

Facelift Surgery Sydney with Dr Kernohan
A facelift is not one standard operation. Different techniques work with facial tissues in different ways, and neck surgery may or may not form part of the plan.
Dr Kernohan assesses which facial layers are contributing before discussing whether facelift surgery is appropriate and, if so, which approach may be considered.
Facelift surgery has limits. It does not directly treat every concern involving the eyelids, brow, skin surface, pigmentation or facial volume. All surgery also carries risks.
Facelift At A Glance
| Topic | General Information |
|---|---|
| Procedure | Facelift / rhytidectomy |
| Surgeon | Dr Michael Kernohan, Specialist Plastic & Reconstructive Surgeon |
| AHPRA registration | MED0001208990 |
| Consultations | Gledswood Hills and Surry Hills |
| Areas assessed | Midface, lower face, jowls, jawline and neck |
| Techniques | Selected according to anatomy |
| Deep plane required? | No |
| Neck surgery required? | No |
| Anaesthetic | Commonly general anaesthesia |
| Incisions | Commonly around the ear and hairline; pattern varies |
| Scars | Permanent |
| Recovery | Varies according to the extent of surgery and individual healing |
| Suitability | Requires individual clinical assessment |
What Is Facelift Surgery?
Facelift surgery, also called rhytidectomy, is an operation used to address selected changes in the face caused by movement of skin and deeper facial tissues over time.
Modern facelift surgery is not based on pulling the skin alone.
Depending on the technique and the patient’s anatomy, surgery may involve:
- Skin
- Superficial fat
- The superficial musculoaponeurotic system, or SMAS
- Deeper facial tissues
- Retaining ligaments
- Lower-face tissues
- Selected neck structures where relevant
The skin is then redraped according to the surgical plan.
The extent of surgery varies from patient to patient.
What Can Facelift Surgery Address?
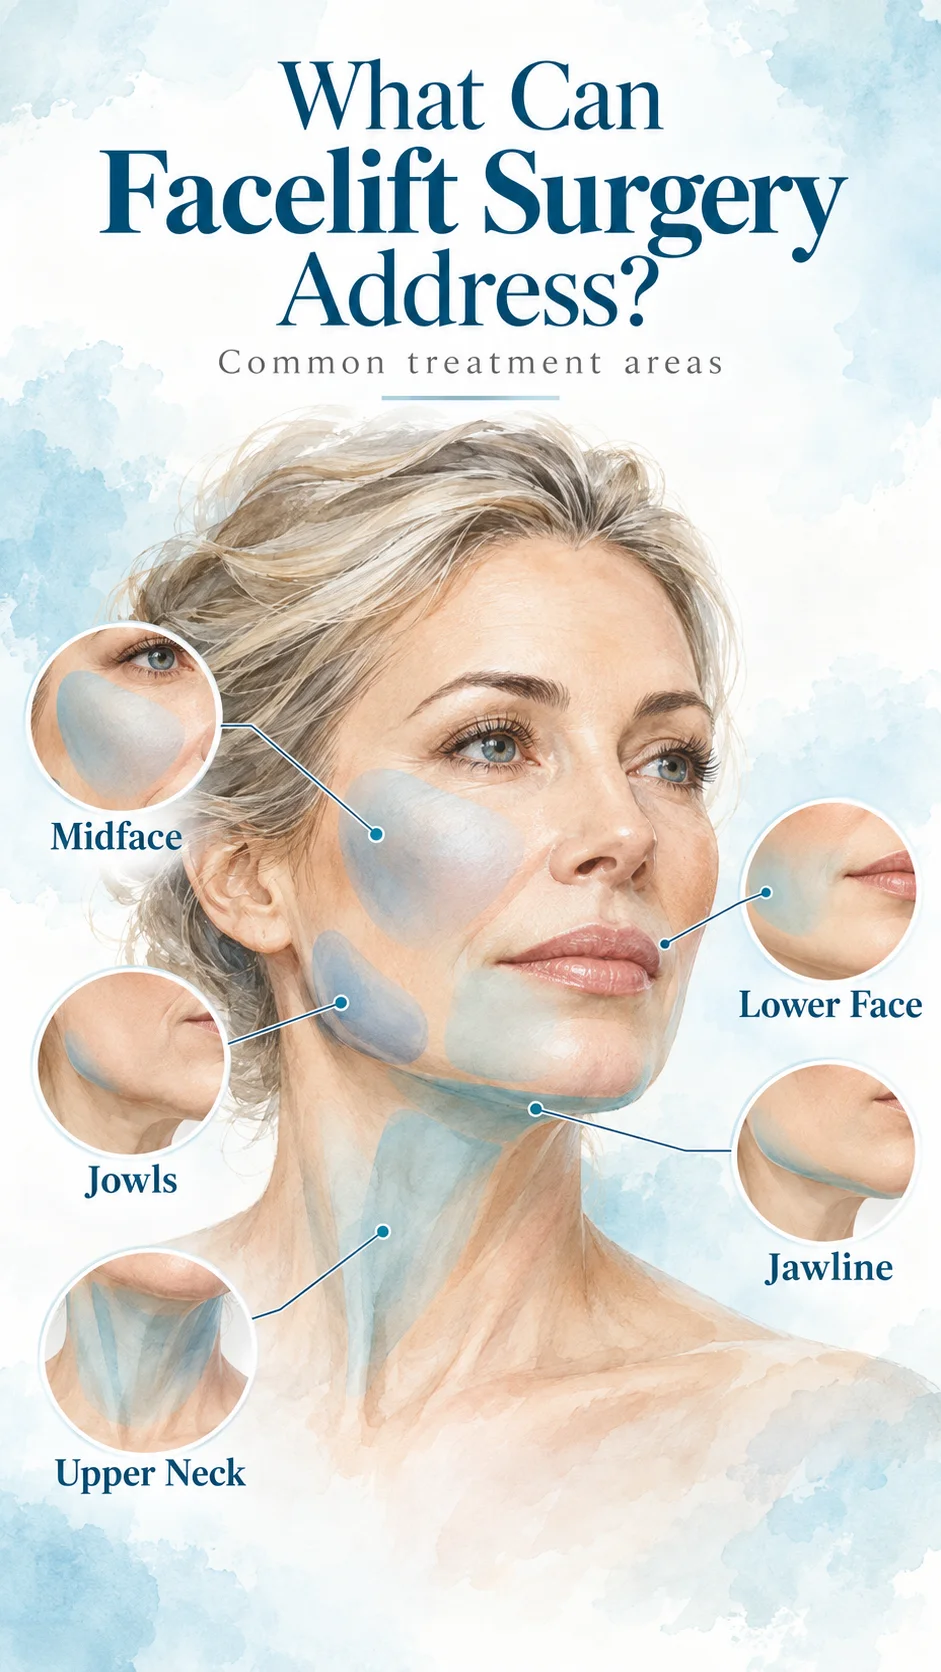
Facelift surgery may be discussed where changes involve deeper facial tissues as well as skin.
✓ Midface
- Changes in cheek tissue position can alter the relationship between the cheek, lower eyelid and folds around the nose and mouth.
- Whether the midface requires treatment depends on the technique and the individual anatomy.
✓ Lower face
- Changes in deeper facial support can contribute to tissue gathering along the lower face.
- Facelift surgery may be considered when these tissues are contributing to the patient’s concern.
✓ Jowls
- Jowls are commonly related to lower-face tissue descent.
- Their appearance may also be influenced by neck and jaw anatomy.
✓ Jawline
- The appearance of the jawline depends on both the lower face and neck.
- For this reason, Dr Kernohan assesses both areas rather than assuming that the concern comes from the face alone.
✓ Upper neck
- Some patients have facial and neck changes together.
- Others do not require a separate neck procedure.
What Can A Facelift Not Address?
Facelift surgery should not be expected to treat every facial concern.
| Concern | Facelift may be relevant? | Separate assessment may be required |
|---|---|---|
| Midface tissue descent | In selected patients | – |
| Lower-face tissue descent | Yes | – |
| Jowls | Commonly assessed | – |
| Jawline changes | Sometimes | Neck anatomy may also contribute |
| Upper-neck changes | Sometimes | Neck lift assessment |
| Upper eyelid skin | No | Upper eyelid assessment |
| Lower eyelid concerns | No | Lower eyelid assessment |
| Brow position | No | Brow surgery assessment |
| Skin pigmentation | No | Skin-focused care |
| Surface skin texture | No | Skin-focused care |
| General facial volume loss | Not directly | Fat transfer or another approach may be discussed |
Understanding these limits is an important part of consultation.

What Dr Michael Kernohan Assesses Before Recommending A Facelift
Dr Michael Kernohan does not select a facelift technique based on the procedure name alone.
He assesses the areas that are contributing to the patient’s concern.
✓ Midface
- Has deeper cheek tissue changed position?
- Would the midface need to be addressed as part of surgery?
✓ Lower face
- Are the changes mainly due to deeper tissue movement, skin, or a combination?
✓ Jowls
- How much of the jowl relates to the lower face, and how much is influenced by the neck?
✓ Jawline
- Is the concern facial, neck-related or both?
✓ Neck
- Are neck skin, platysma bands, superficial fat or deeper tissues contributing?
✓ SMAS and deeper facial tissues
- Which tissue layers appear to require treatment?
✓ Skin
- How much skin needs to be redraped after the deeper tissues are addressed?
✓ Hairline and ears
- These features affect incision planning.
✓ Facial asymmetry
- Most faces are not completely symmetrical before surgery.
- Pre-existing differences are identified during consultation.
✓ Previous procedures
Dr Kernohan will ask about previous:
- Facelift surgery
- Neck lift surgery
- Dermal fillers
- Fat transfer
- Threads
- Eyelid surgery
- Other facial operations
Previous procedures can alter tissue planes, scars and surgical planning.
✓ General health
Assessment also considers:
- Medical history
- Current medicines
- Supplements
- Nicotine exposure
- Blood pressure
- Bleeding risk
- Anaesthetic history
- Recovery support
The operation should be selected for the patient’s anatomy rather than fitting every patient into one named technique.


How Do Facelift Techniques Differ?
Facelift techniques differ according to the tissue layers being treated and how those tissues are mobilised.
Two terms patients commonly encounter are:
- SMAS facelift
- Deep plane facelift
These are not the only possible approaches.
The appropriate technique depends on the patient’s anatomy, previous surgery and the areas being addressed.
What Does SMAS Mean?
SMAS stands for superficial musculoaponeurotic system.
It is a fibromuscular tissue layer beneath the skin.
Different facelift techniques may:
- Reposition the SMAS
- Fold it
- Tighten selected areas
- Release parts of the surrounding support structures
There are several recognised SMAS-based approaches.
Patients comparing techniques can read more about the differences between deep plane and SMAS facelift approaches.
What Does Deep Plane Mean?
Deep plane facelift surgery involves selected dissection beneath the SMAS.
Depending on the surgical plan, selected retaining ligaments may be released so that deeper tissues can be mobilised.
The term refers to the anatomical plane of dissection.
It does not mean that the operation is automatically preferable to a SMAS-based facelift.
Deep Plane Versus SMAS Facelift
Both approaches work with deeper facial support structures.
| Feature | Deep Plane Approach | SMAS-Based Approach |
|---|---|---|
| Tissue plane | Beneath selected areas of the SMAS | Works with or on the SMAS |
| Retaining ligaments | May be selectively released | Depends on technique |
| Tissue movement | Deeper tissues may move as a connected unit | SMAS may be folded, lifted or repositioned |
| Skin | Redraped after deeper work | Redraped after deeper work |
| Neck | Assessed separately | Assessed separately |
| Suitability | Individual | Individual |
Current research does not establish that one approach is appropriate for every patient.
Technique selection should therefore be individual.
Facelift Versus Neck Lift
A facelift and neck lift address different but sometimes overlapping anatomy.
| Concern | Facelift | Neck Lift |
|---|---|---|
| Midface tissue descent | May address | No |
| Lower-face tissue descent | Primary area | No |
| Jowls | Commonly assessed | Limited if lower-face descent is the main cause |
| Jawline | Facial component | Neck component |
| Neck skin | May be included | Primary consideration |
| Platysma bands | May be addressed where neck surgery is included | Commonly assessed |
| Under-chin region | May be included | Commonly assessed |
| Deeper neck fullness | Separate assessment | Separate deep-neck assessment may be required |
Some patients mainly need facial surgery.
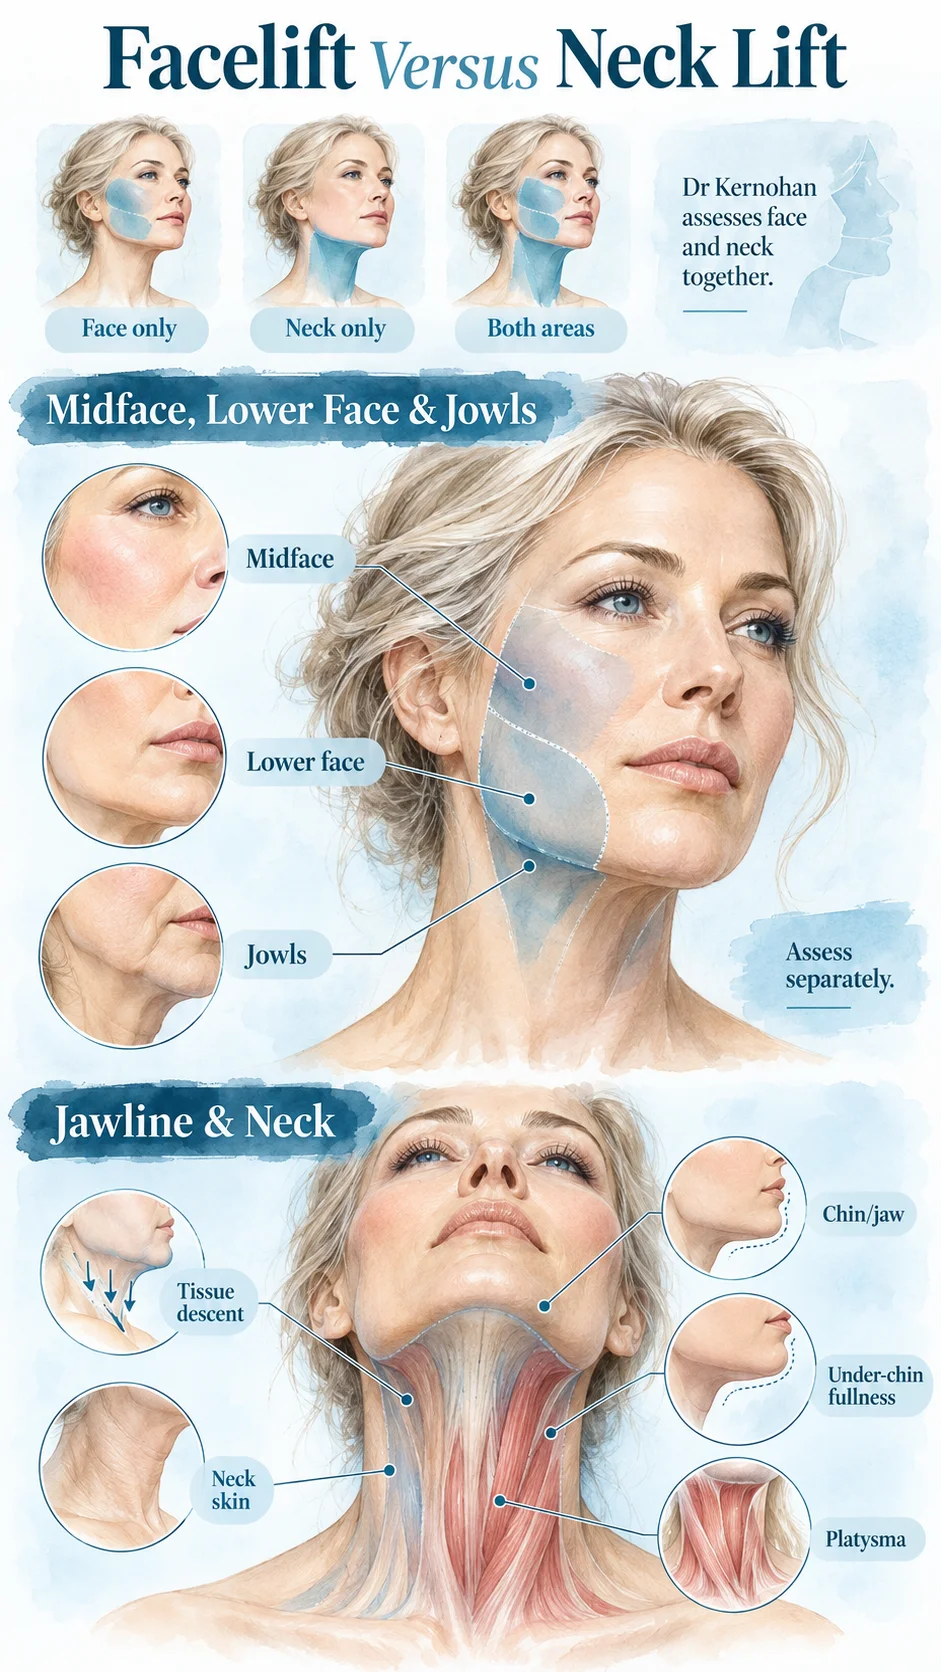
Others mainly need neck surgery.
Some have changes involving both.
Dr Kernohan assesses the face and neck together before discussing whether either area requires treatment.
Midface, Lower Face And Jowls
Patients often use the word “facelift” to describe several different facial concerns.
These should be assessed separately.
✓ Midface
This includes deeper cheek tissues and their relationship to the lower eyelid and nasolabial region.
✓ Lower face
This includes the tissues around the mouth, lower cheek and jawline.
✓ Jowls
Jowls usually relate to lower-face tissue descent but can appear more prominent when neck anatomy also changes.
Surgery should therefore be planned around the structures contributing to the concern rather than one visible feature alone.
Jawline And Neck Relationship
The jawline sits at the junction between the lower face and neck.
Changes in either area can alter its appearance.
For example:
- Lower-face tissue descent can contribute to jowls.
- Neck skin can affect the jaw-to-neck transition.
- Platysma changes can influence the upper neck.
- Submental fullness can affect the area beneath the chin.
- Chin and jaw relationships can also influence the overall appearance.
A facelift alone cannot address every cause of a jawline concern.
Previous Fillers, Threads Or Facial Surgery
Previous facial procedures are relevant to facelift planning.
Patients should tell Dr Kernohan about previous:
- Dermal fillers
- Fat transfer
- Thread procedures
- Facelift surgery
- Neck lift surgery
- Eyelid surgery
- Facial implants
- Other facial procedures
Where available, details about the product, date and treatment area can be helpful.
Previous procedures may alter:
- Tissue volume
- Scar tissue
- Tissue planes
- Skin
- Facial asymmetry
They do not automatically prevent facelift surgery, but they may affect planning.
Where Are Facelift Incisions?
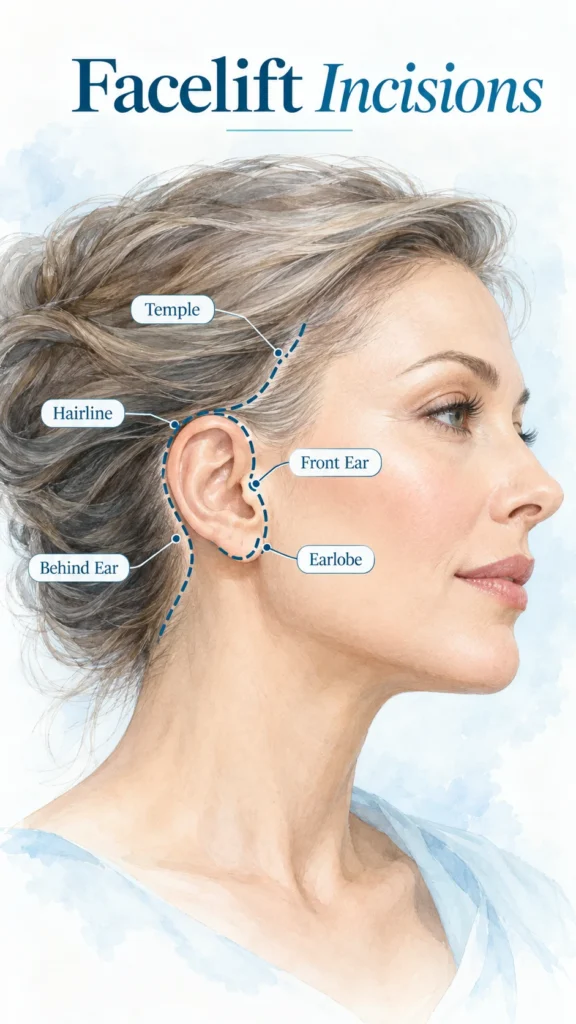
Incision placement varies according to the planned operation.
Possible locations include:
- The temporal hairline
- The area immediately in front of the ear
- Around the earlobe
- Behind the ear
- The posterior hairline
A separate incision beneath the chin may sometimes be used where neck surgery is included.
Not every patient requires every incision.
Planning depends on:
- Hairline
- Sideburn position
- Ear anatomy
- Skin excess
- Neck involvement
- Previous scars
- Previous facelift surgery
What Should I Know About Facelift Scars?
Facelift scars are permanent.
Their appearance changes during healing and scar maturation.
Factors influencing scars include:
- Genetics
- Skin
- Scar tension
- Wound healing
- Infection
- Nicotine exposure
- Previous scars
- Previous surgery
Some scars may remain noticeable.
Raised, widened or otherwise prominent scars can occur.
Hairline changes and hair loss close to an incision are also recognised considerations.
Click to Download Dr Michael Kernohan’s Facelift Surgery Guide

Why Does Facial Nerve Anatomy Matter?
Branches of the facial nerve control facial movement.
These branches travel through defined anatomical pathways within the face.
Facelift surgery involves tissue planes close to some of these structures.
Temporary weakness can occur after surgery.
Longer-term facial nerve injury is less common but remains an important risk.
Individual risk depends on factors including:
- Anatomy
- Surgical technique
- Extent of surgery
- Previous operations
- Scar tissue
This is one reason detailed anatomical planning is important.
Risks And Possible Complications

All facelift surgery carries risks. Possible complications include:
- Bleeding
- Haematoma
- Infection
- Delayed wound healing
- Wound separation
- Skin healing problems
- Skin loss
- Fluid collection
- Permanent scars
- Raised or widened scars
- Numbness
- Changes in sensation
- Temporary facial weakness
- Longer-term facial nerve injury
- Facial asymmetry
- Hair loss near incisions
- Hairline change
- Earlobe change
- Contour differences
- Pain
- Anaesthetic complications
- Blood clots
- Need for additional treatment
- Further surgery
The risks relevant to an individual patient depend on the operation, health, anatomy and other factors.
Measures are taken to reduce avoidable risk, but complications cannot be eliminated.
Expected Early Changes After Facelift Surgery
Some postoperative changes are expected during early healing.
These may include:
- Swelling
- Bruising
- Tightness
- Tenderness
- Numbness
- Altered skin sensation
- Temporary firmness
- Differences between the two sides while swelling settles
The extent and duration vary.
These expected changes should be distinguished from complications requiring review.
How Is Facelift Surgery Planned?
The exact operation depends on the surgical technique selected.
Steps may include:
- General anaesthesia and surgical monitoring
- Planned incisions
- Elevation of selected tissue layers
- Treatment of the SMAS or deeper facial tissues
- Release of selected retaining ligaments where relevant
- Repositioning of facial tissues
- Neck treatment where included
- Skin redraping
- Removal of selected excess skin
- Closure of incisions
- Dressings and, in selected cases, drains
This is not an identical sequence for every patient.
The extent of surgery can differ substantially depending on the face, neck, previous procedures and chosen technique.
Take The Quiz
Anaesthesia And Surgical Facility
Facelift surgery is commonly performed under general anaesthesia.
The surgical facility depends on the planned procedure and individual circumstances.
Dr Michael Kernohan operates at:
- The George Centre, Gledswood Hills
- Camden Surgical Hospital
- St Vincent’s Hospital by request only
How Long Do Changes After Facelift Surgery Last?
A fixed number of years cannot be guaranteed.
Facelift surgery changes facial anatomy at a particular point in time.
Ageing then continues.
Long-term appearance can be affected by:
- Skin
- Tissue quality
- Genetics
- Weight change
- Health
- Sun exposure
- Nicotine exposure
- Surgical technique
- Further changes in the face and neck
Some patients may consider additional surgery later. Others may not. The long-term course differs between individuals.
Patients who want more detail about how ageing, skin quality, weight change and surgical technique can influence long-term changes can read our guide to facelift longevity.
Recovery After Facelift Surgery
Recovery varies according to:
- Facelift technique
- Extent of surgery
- Whether neck surgery is included
- Previous facial surgery
- Other procedures performed
- Individual healing
Early recovery after facelift surgery may include:
- Swelling
- Bruising
- Tightness
- Tenderness
- Numbness
Patients receive individual instructions regarding:
- Wound care
- Hair washing
- Sleeping
- Driving
- Work
- Exercise
- Lifting
- Medicines
- Follow-up
Patients should follow their written postoperative instructions rather than relying on a fixed online timetable.
When Should Patients Contact The Surgical Team?
Patients receive information about symptoms that require review.
These may include:
- Rapidly increasing swelling
- Marked one-sided swelling
- Unexpected bleeding
- Increasing pain
- Increasing redness
- Wound discharge
- Skin colour change
- Wound opening
- Fever
- Feeling generally unwell
- New facial weakness
Rapid facial or neck swelling can indicate a haematoma and requires prompt assessment.
Can Other Procedures Be Performed With A Facelift?
Another procedure may sometimes be considered where it addresses a separate anatomical concern.
Examples may include, where clinically appropriate:
- Neck lift surgery
- Upper eyelid surgery
- Lower eyelid surgery
- Brow surgery
- Selected facial fat transfer
Combining procedures increases the extent of surgery and may alter recovery and risk.
Additional procedures should therefore be considered for a specific clinical reason rather than added routinely.
What Happens At A Facelift Consultation?
Consultation begins by discussing what the patient has noticed and what they want to understand.
Dr Kernohan may ask about:
- Medical history
- Medicines
- Supplements
- Allergies
- Nicotine exposure
- Blood pressure
- Bleeding history
- Anaesthetic history
- Previous facial surgery
- Previous fillers
- Threads
- Fat transfer
- Previous complications
- Recovery circumstances
Assessment may include:
- Midface
- Lower face
- Jowls
- Jawline
- Neck
- Skin
- Facial movement
- Facial asymmetry
- Hairline
- Ear anatomy
- Previous scars
The consultation can then address whether:
- Facelift surgery may be relevant
- A deep plane approach may be considered
- A SMAS-based approach may be considered
- Neck surgery should be discussed
- Another facial procedure is relevant
- Surgery should be delayed
- Further medical assessment is needed
- Surgery should not proceed
A consultation does not commit the patient to surgery.
What To Bring To Your Facelift Consultation
Where relevant, bring:
- A current medicines list
- Details of medical conditions
- Details of previous facial surgery
- Previous operative reports if available
- Information about fillers
- Details of thread procedures
- Information about previous facial implants
- Details of previous complications
- Questions about scars, risks and recovery
It is also useful to consider practical recovery issues such as:
- Work
- Caring responsibilities
- Transport
- Support at home
- Follow-up travel
Questions To Ask At Your Consultation
Useful questions include:
- Which areas of my face are causing the changes I have noticed?
- Which facelift technique are you considering and why?
- Would a SMAS-based approach be relevant?
- Would a deep plane approach be relevant?
- Does my neck need separate treatment?
- Where will my scars be?
- How could my previous fillers or surgery affect the operation?
- Which risks are most relevant to my anatomy?
- What will the facelift not address?
- What recovery restrictions will apply?
- Could surgery need to be staged?

Facelift Consultations In Sydney And South-West Sydney
Dr Michael Kernohan consults at:
- Gledswood Hills
South-West Sydney - Surry Hills
Sydney
He operates at:
- The George Centre, Gledswood Hills
- Camden Surgical Hospital, Elderslie
- St Vincent’s Hospital by request only
Patients travelling for facelift surgery should plan for:
- Transport after surgery
- Support during early recovery
- Follow-up appointments
- Time away from work
- Caring responsibilities
- Travel between home and the consulting rooms
Patients travelling from Camden, Campbelltown, surrounding areas of South-West Sydney, the Southern Highlands or regional New South Wales should discuss follow-up arrangements before surgery.
Facelift Surgery Costs
Facelift surgery is planned individually.
Fees can vary according to:
- Technique
- Extent of facial surgery
- Whether neck surgery is included
- Whether another procedure is performed
- Operating time
- Anaesthetist fees
- Surgical facility fees
A personalised written estimate can be provided after consultation once the proposed operation has been established. For more detail about the factors that can influence the overall fee, see our guide to facelift cost in Sydney.
Before-And-After Photographs: Facelift Before and After Photo

Disclaimer: All surgical or invasive procedures come with inherent risks, and results can vary widely between individuals due to factors like lifestyle, anatomy, overall health, weight, and nutrition. We encourage you to conduct thorough research and consider seeking a second opinion from a qualified healthcare provider.
Before-and-after photographs may help patients understand differences in starting anatomy and surgical planning.
They cannot predict another patient’s outcome.
Differences between cases may relate to:
- Midface anatomy
- Lower-face tissue position
- Neck anatomy
- Skin
- Previous surgery
- Age
- Health
- Procedure performed
- Individual healing
Images should be viewed as examples of individual clinical cases rather than expected outcomes.
About Dr Michael Kernohan
Dr Michael Kernohan is an AHPRA-registered Specialist Plastic & Reconstructive Surgeon and Fellow of the Royal Australasian College of Surgeons, FRACS (Plast).
His qualifications include:
- MBBS – Bachelor of Medicine, Bachelor of Surgery
University of Newcastle-upon-Tyne, 2000. CLIK - MSc – Master of Science
University of Newcastle-upon-Tyne, 2007, with research in speech and swallowing. Plastic Surgery Hub - BDS – Bachelor of Dental Surgery
University of Glasgow, 1994. CLIK - MRCS – Member of the Royal College of Surgeons
Royal College of Surgeons of Edinburgh, 2003. MRCS is a postgraduate surgical qualification demonstrating achievement of the core knowledge and competencies required to progress through specialist surgical training. Royal College of Surgeons - FDSRCS – Fellow in Dental Surgery of the Royal College of Surgeons
Royal College of Surgeons of Edinburgh, 1997. This postgraduate dental surgical fellowship reflects further training and assessment beyond the primary dental degree. Royal College of Surgeons - FRCS (Plast) – Fellow of the Royal College of Surgeons in Plastic Surgery
Intercollegiate UK qualification, awarded in 2008. This denotes specialist-level surgical training and examination in Plastic Surgery within the UK system. Plastic Surgery Hub - FRACS (Plast) – Fellow of the Royal Australasian College of Surgeons in Plastic and Reconstructive Surgery
Awarded in Australia in 2016. This is the specialist surgical fellowship associated with recognised training in Plastic and Reconstructive Surgery in Australia and New Zealand.
His AHPRA registration number is MED0001208990.
Dr Kernohan consults at Gregory Hills and Surry Hills.
His practice includes plastic and reconstructive surgery of the face, breast and body, along with reconstructive surgery following trauma, skin cancer and other conditions.
Medical review
Medically reviewed by Dr Michael Kernohan
AHPRA-registered Specialist Plastic & Reconstructive Surgeon
FRACS (Plast)
AHPRA registration: MED0001208990
Last medically reviewed: September 2026
Summary
Facelift surgery is a group of surgical techniques used to address selected changes in the midface, lower face and jawline.
Patients considering facelift surgery should understand that:
- A facelift is not one standard operation.
- Deep plane and SMAS are different technical approaches within facelift surgery.
- One technique is not automatically preferable for every patient.
- Neck surgery is not required for everyone.
- A facelift cannot directly treat every eyelid, brow, skin or volume concern.
- Incisions and scars are permanent.
- Facial nerve changes are recognised risks.
- Haematoma and wound-healing problems can occur.
- Recovery varies.
- Ageing continues after surgery.
- A fixed duration of change cannot be guaranteed.
- Further surgery may sometimes be required.
Dr Michael Kernohan assesses the face, neck, previous procedures, health and individual concerns before discussing whether facelift surgery and which approach may be relevant.

FAQs About Facelift Surgery
Discuss Facelift Surgery With Dr Michael Kernohan
A consultation can help determine which anatomical structures are contributing to a patient’s concerns and whether facelift surgery should be considered.
Dr Michael Kernohan can assess:
- Midface
- Lower face
- Jowls
- Jawline
- Neck
- SMAS and deeper facial tissues
- Previous fillers
- Previous threads
- Previous facial surgery
- Incisions and scars
- Surgical risks
- Recovery considerations
- Whether another procedure may be relevant
Further Reading
- Read more about Deep Plane Facelift NSW
- Read more about Partial Facelift Surgery NSW
- Read more about Revision Facelift Sydney
- Read more about Male facelift South West Sydney
- Read Dr Michael Kernohan’s Blog on Facelift Recovery
- Read Dr Michael Kernohan’s Info Page on Facelift Cost Sydney
- Read Dr Michael Kernohan’s Blog on How to Prepare for Surgery in Sydney